




1- Faculty of Financial Sciences, Management and Entrepreneurship, University of Kashan, Kashan, Iran.
2- Department of Business Administration, Faculty of Financial Sciences, Management and Entrepreneurship, University of Kashan, Kashan, Iran. ,drmazroui@kashanu.ac.ir
2- Department of Business Administration, Faculty of Financial Sciences, Management and Entrepreneurship, University of Kashan, Kashan, Iran. ,
Full-Text [PDF 1479 kb]
(77 Downloads)
| Abstract (HTML) (245 Views)
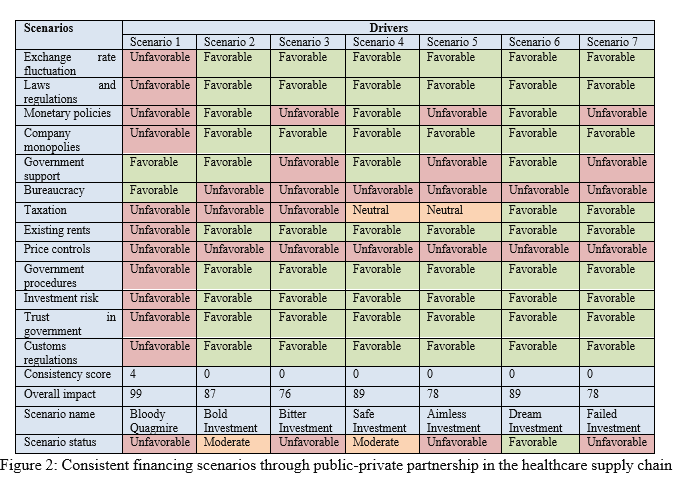
In Scenario Wizard, scenarios are considered strongly consistent if their consistency score is at least zero. Other scenarios, due to internal inconsistency, cannot represent a plausible future for financing through public-private partnership. The analysis revealed seven strongly consistent scenarios.
According to Figure 2, Scenario 6 is considered the most favorable in terms of public-private partnership. In contrast, Scenarios 2 and 3 represent moderate positions, characterized by a mix of favorable, neutral, and unfavorable conditions. Scenarios 1, 3, 5, and 7 are categorized as unfavorable due to their predominantly negative conditions. An examination of the remaining scenarios showed that out of 91 possible states across the 7 consistent scenarios, 58 states (63%) lead to increased investment, while 31 states (34%) result in decreased investment. Furthermore, 6 of the 7 consistent scenarios (85%) lead to increased investment and improved financing, whereas 1 scenario (15%) results in decreased investment and weakened financing.
Discussion
Scenario Six, referred to as “Dream Investment,” is considered favorable due to the fact that most of its drivers are in a favorable state. In contrast, the other scenarios are less favorable, with Scenario One identified as entirely unfavorable. In Scenario Six, healthcare financing through public-private partnerships occupies an optimal position. To realize this scenario, the government must create a secure and appealing environment that encourages investor participation. This requires the implementation of tailored fiscal and monetary policies specific to the healthcare sector. Exchange rate management and fiscal policy can play a pivotal role. If the exchange rate remains stable and financial policies are designed to facilitate investment and support industry growth, they can effectively attract investors. Moreover, regulatory transparency and predictability significantly contribute to building trust and encouraging investment. These conditions promote confidence among investors and private entities. Reducing bureaucratic obstacles and liberalizing private sector operations can further advance the growth and dynamism of the healthcare industry by creating additional opportunities for investment and expansion.
However, as Scenario Six also illustrates, excessive administrative bureaucracy and government-imposed price controls continue to pose challenges. To mitigate these issues, the government should adopt measures such as outsourcing selected functions, emphasizing competitive advantages, streamlining administrative chains of command, and delegating authority. Additionally, reducing price controls while subsidizing healthcare for the public and enabling open competition among hospitals can not only enhance service quality but also promote more competitive pricing.
Based on the findings of this study—including the macro-level categorization of drivers and the results of scenario analysis—it is recommended that future research focus on improving economic-financial factors under heightened environmental uncertainty, strengthening regulatory dimensions with an emphasis on information transparency, and developing strategies to streamline the public healthcare bureaucracy.
Research Limitations
Conclusion
This research, by identifying 21 drivers and extracting 13 key drivers, outlined 7 consistent scenarios for the future of financing through public-private partnership in Iran's healthcare supply chain. The "Dream Investment" scenario, as the most desirable scenario, indicates that exchange rate stability, transparency of laws and regulations, reduction of company monopolies, stability of government procedures, reduction of investment risk, and trust-building between the public and private sectors are the most critical factors for attracting investment. In contrast, mandatory pricing, administrative bureaucracy, and high taxes were identified as persistent structural barriers in all scenarios, highlighting the necessity of their reform. Given that 85% of the consistent scenarios lead to increased investment, policymakers are recommended to adopt coordinated monetary and fiscal policies, reduce administrative bureaucracy, replace mandatory pricing with competitive mechanisms, and provide treatment subsidies to the public to pave the way for the realization of the desirable scenario.
Declarations
Ethical considerations: This study was conducted following approval by the Research Ethics Committee of the University of Kashan (Ethics Approval Code: IR.KASHANU.REC.1402.018).
Funding: This research was conducted independently and without receiving any financial support.
Conflict of interest: The authors declare that there is no financial, organizational, or personal conflict of interest in connection with this study.
Authors’ contribution: Mohammadreza Safari: Data curation, Resources, Data management, Writing– original draft, Writing– review & editing, Visualization, Project administration, Fund acquisition
Esmaeil Mazroui Nasrabadi: Conceptualization, Study design, Methodology, Software, Validation, Data analysis, Writing– original draft, Writing– review & editing, Visualization, Supervision, Project administration, Fund acquisition, Final approval
All authors have read and approved the final version of the manuscript.
Consent for publication: Not applicable.
Data availability: Access to the data is available through the corresponding author upon reasonable request.
AI declaration: The authors used artificial intelligence (Deepseek-V3) for editing the English section of this article. All AI-edited content has been reviewed and approved by the authors.
Acknowledgements: Thank you to all the participants in this research.
Full-Text: (12 Views)
Introduction
The health sector is widely regarded as one of the main drivers of national growth [1]. Among its most pressing challenges are the escalating costs of healthcare. Between 2000 and 2021, healthcare expenditures increased sharply; notably, from 2015 to 2020, these costs nearly quadrupled [2]. Healthcare expenses affect low-income households in two significant ways: not only must they spend considerable sums on medical care, but they are also unable to earn income during periods of illness. Beyond direct medical costs such as medications, diagnostic tests, and consultation fees, patients also face substantial indirect expenses—including transportation, accommodation, and food [3]. In light of this, the health sector must adopt optimized financing strategies to reduce overall expenditures and ease the financial burden on families.
The primary objective of public-private partnerships (PPPs) is to promote infrastructure development [4] and infrastructure projects [5] by leveraging resources and expertise to execute socially significant projects at the lowest possible cost and risk while providing high-quality services to economic units [6]. PPPs are also widely utilized in the health and care sectors, offering various benefits such as regional development [7], enhanced innovation [8], improved quality [9], addressing social inequality [10], increasing access to and affordability of services [11], and supporting maternal, newborn, and child healthcare [12]. The COVID-19 pandemic [13] has significantly increased investment in these sectors, as it has heightened public and private focus on health and care financing.
Iran’s healthcare system is less developed compared to that of developed nations [14]. It faces numerous challenges, including inefficient information infrastructure [15], the absence of a structured framework for identifying and prioritizing key health concerns [16], volatility in public health budget allocations [1], and financing difficulties [17]. These issues underscore the growing need to involve the private sector in addressing both hardware-related challenges (such as deficiencies in information infrastructure, financial systems, and equipment) and software-related challenges (such as procedural inefficiencies and managerial practices). Despite this need, public-private partnerships (PPP) in this area have received limited attention, and a number of problems persist—such as non-compliance with agreements (due to changing conditions), incomplete project implementation, and hospital post-construction disputes. These challenges underscore the need for a more thorough investigation into PPPs in Iran’s healthcare sector.
Previous research in this field can be divided into several categories. The first category includes studies that have examined issues related to public-private partnerships (PPPs) in this field. In this context, the research by Ganji Arjanaki and Mazrouei Nasrabadi [18] can be highlighted, which identified 23 drivers, grouped into 8 categories, for PPPs in the Iranian healthcare supply chain. The second category comprises studies adopting a futures research approach to financing the healthcare supply chain. Here, the research by Safari and Mazrouei Nasrabadi [17] is notable, as it explored the future of financing the healthcare supply chain through service provision and identified 15 scenarios, categorized into successors, followers, and leaders. The next study, also by Safari and Mazrouei Nasrabadi [1], focused on the futures research of financing the healthcare supply chain through government assistance. This study identified five scenarios: wealthy government, calmly inefficient, unplanned inefficient, unstable inefficient, and bankrupt
Methods
This study employed a mixed-methods approach—quantitative and qualitative—and was conducted in four phases to explore the future of public-private partnerships (PPP) in Iran's healthcare supply chain. Participants in all phases were experts in Iran's healthcare supply chain, including individuals with at least 10 years of relevant experience or university faculty specializing in management disciplines and active in healthcare research. Sampling in all phases was judgmental and continued using the snowball sampling technique.
Phase One: Objective: Identifying the key drivers of financing through PPPs. Sample size: Based on theoretical saturation of expert input. Data collection instrument: Semi-structured interviews. Analysis method: Thematic analysis. Rigor assessment: Guba and Lincoln's four criteria.
Dependability: An audit trail was used, and the collected data were reviewed and evaluated by an external auditor. Credibility: Coding results were reviewed by participants; participants represented diverse experiences (from various levels of the healthcare supply chain); sampling continued until theoretical saturation was achieved. Confirmability: The research process was documented, confirmed by two university professors, and fully detailed in the research output. Transferability: Participant characteristics were reported to support the transferability of findings to other research settings.
Phase Two: Objective: Examining relationships and identifying key drivers. Sample size: 12 participants. Data collection instrument: Researcher-designed questionnaire. Analysis method: MicMac analysis. Rigor assessment: Face validity (confirmed by university faculty). For each relationship between the drivers, the value with the highest frequency was selected, and at least 60% of experts had to agree on the stated value for each relationship.
Phase Three: Objective: Identifying key uncertainties. Sample size: 12 participants. Data collection instrument: Interview. Analysis method: Interactive management. Rigor assessment: Minimum 60% consensus among participants.
Phase Four: Objective: Scenario development. Sample size: 12 participants. Data collection instrument: Researcher-designed questionnaire. Analysis method: Scenario Wizard software. Rigor assessment: Face validity (confirmed by university faculty). For each relationship between the drivers, the value with the highest frequency was selected, and at least 60% of experts had to agree on the stated value for each relationship. Scenario consistency was assessed using Scenario Wizard software.
Results
In the initial phase of the study, 21 influencing factors were identified through interviews with 15 experts from academic and healthcare sectors, using thematic analysis. The drivers identified through these interviews are listed in Table 1.

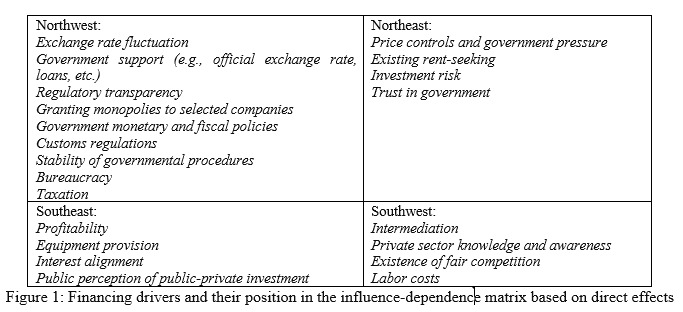
In the second phase, a researcher-designed questionnaire was distributed among 12 experts. The responses were then analyzed using MicMac software. The results, which show the status of key drivers, are presented in Figure 1.
The health sector is widely regarded as one of the main drivers of national growth [1]. Among its most pressing challenges are the escalating costs of healthcare. Between 2000 and 2021, healthcare expenditures increased sharply; notably, from 2015 to 2020, these costs nearly quadrupled [2]. Healthcare expenses affect low-income households in two significant ways: not only must they spend considerable sums on medical care, but they are also unable to earn income during periods of illness. Beyond direct medical costs such as medications, diagnostic tests, and consultation fees, patients also face substantial indirect expenses—including transportation, accommodation, and food [3]. In light of this, the health sector must adopt optimized financing strategies to reduce overall expenditures and ease the financial burden on families.
The primary objective of public-private partnerships (PPPs) is to promote infrastructure development [4] and infrastructure projects [5] by leveraging resources and expertise to execute socially significant projects at the lowest possible cost and risk while providing high-quality services to economic units [6]. PPPs are also widely utilized in the health and care sectors, offering various benefits such as regional development [7], enhanced innovation [8], improved quality [9], addressing social inequality [10], increasing access to and affordability of services [11], and supporting maternal, newborn, and child healthcare [12]. The COVID-19 pandemic [13] has significantly increased investment in these sectors, as it has heightened public and private focus on health and care financing.
Iran’s healthcare system is less developed compared to that of developed nations [14]. It faces numerous challenges, including inefficient information infrastructure [15], the absence of a structured framework for identifying and prioritizing key health concerns [16], volatility in public health budget allocations [1], and financing difficulties [17]. These issues underscore the growing need to involve the private sector in addressing both hardware-related challenges (such as deficiencies in information infrastructure, financial systems, and equipment) and software-related challenges (such as procedural inefficiencies and managerial practices). Despite this need, public-private partnerships (PPP) in this area have received limited attention, and a number of problems persist—such as non-compliance with agreements (due to changing conditions), incomplete project implementation, and hospital post-construction disputes. These challenges underscore the need for a more thorough investigation into PPPs in Iran’s healthcare sector.
Previous research in this field can be divided into several categories. The first category includes studies that have examined issues related to public-private partnerships (PPPs) in this field. In this context, the research by Ganji Arjanaki and Mazrouei Nasrabadi [18] can be highlighted, which identified 23 drivers, grouped into 8 categories, for PPPs in the Iranian healthcare supply chain. The second category comprises studies adopting a futures research approach to financing the healthcare supply chain. Here, the research by Safari and Mazrouei Nasrabadi [17] is notable, as it explored the future of financing the healthcare supply chain through service provision and identified 15 scenarios, categorized into successors, followers, and leaders. The next study, also by Safari and Mazrouei Nasrabadi [1], focused on the futures research of financing the healthcare supply chain through government assistance. This study identified five scenarios: wealthy government, calmly inefficient, unplanned inefficient, unstable inefficient, and bankrupt
Methods
This study employed a mixed-methods approach—quantitative and qualitative—and was conducted in four phases to explore the future of public-private partnerships (PPP) in Iran's healthcare supply chain. Participants in all phases were experts in Iran's healthcare supply chain, including individuals with at least 10 years of relevant experience or university faculty specializing in management disciplines and active in healthcare research. Sampling in all phases was judgmental and continued using the snowball sampling technique.
Phase One: Objective: Identifying the key drivers of financing through PPPs. Sample size: Based on theoretical saturation of expert input. Data collection instrument: Semi-structured interviews. Analysis method: Thematic analysis. Rigor assessment: Guba and Lincoln's four criteria.
Dependability: An audit trail was used, and the collected data were reviewed and evaluated by an external auditor. Credibility: Coding results were reviewed by participants; participants represented diverse experiences (from various levels of the healthcare supply chain); sampling continued until theoretical saturation was achieved. Confirmability: The research process was documented, confirmed by two university professors, and fully detailed in the research output. Transferability: Participant characteristics were reported to support the transferability of findings to other research settings.
Phase Two: Objective: Examining relationships and identifying key drivers. Sample size: 12 participants. Data collection instrument: Researcher-designed questionnaire. Analysis method: MicMac analysis. Rigor assessment: Face validity (confirmed by university faculty). For each relationship between the drivers, the value with the highest frequency was selected, and at least 60% of experts had to agree on the stated value for each relationship.
Phase Three: Objective: Identifying key uncertainties. Sample size: 12 participants. Data collection instrument: Interview. Analysis method: Interactive management. Rigor assessment: Minimum 60% consensus among participants.
Phase Four: Objective: Scenario development. Sample size: 12 participants. Data collection instrument: Researcher-designed questionnaire. Analysis method: Scenario Wizard software. Rigor assessment: Face validity (confirmed by university faculty). For each relationship between the drivers, the value with the highest frequency was selected, and at least 60% of experts had to agree on the stated value for each relationship. Scenario consistency was assessed using Scenario Wizard software.
Results
In the initial phase of the study, 21 influencing factors were identified through interviews with 15 experts from academic and healthcare sectors, using thematic analysis. The drivers identified through these interviews are listed in Table 1.
In the second phase, a researcher-designed questionnaire was distributed among 12 experts. The responses were then analyzed using MicMac software. The results, which show the status of key drivers, are presented in Figure 1.
According to Figure 1, the horizontal axis represents the dependence level of each driver, while the vertical axis represents its influence level. The drivers are categorized into four groups: independent, linkage, autonomous, and dependent. In the upper-right quadrant, 4 independent drivers are positioned. The upper-left quadrant includes 9 linkage drivers. The lower-right quadrant contains 4 autonomous drivers, and the lower-left quadrant includes 4 dependent drivers.
In the third phase, interactive management sessions were held to identify the uncertainties (states) associated with each financing driver. As a result, 29 potential states were defined for 13 drivers, all classified along a spectrum ranging from favorable to unfavorable.
In the fourth and final phase, a specially designed questionnaire was used to collect expert opinions, with responses ranging from -3 to +3. These data were analyzed using Scenario Wizard software. The results, indicating the consistent scenarios, are presented in Figure 2.
In the third phase, interactive management sessions were held to identify the uncertainties (states) associated with each financing driver. As a result, 29 potential states were defined for 13 drivers, all classified along a spectrum ranging from favorable to unfavorable.
In the fourth and final phase, a specially designed questionnaire was used to collect expert opinions, with responses ranging from -3 to +3. These data were analyzed using Scenario Wizard software. The results, indicating the consistent scenarios, are presented in Figure 2.
In Scenario Wizard, scenarios are considered strongly consistent if their consistency score is at least zero. Other scenarios, due to internal inconsistency, cannot represent a plausible future for financing through public-private partnership. The analysis revealed seven strongly consistent scenarios.
According to Figure 2, Scenario 6 is considered the most favorable in terms of public-private partnership. In contrast, Scenarios 2 and 3 represent moderate positions, characterized by a mix of favorable, neutral, and unfavorable conditions. Scenarios 1, 3, 5, and 7 are categorized as unfavorable due to their predominantly negative conditions. An examination of the remaining scenarios showed that out of 91 possible states across the 7 consistent scenarios, 58 states (63%) lead to increased investment, while 31 states (34%) result in decreased investment. Furthermore, 6 of the 7 consistent scenarios (85%) lead to increased investment and improved financing, whereas 1 scenario (15%) results in decreased investment and weakened financing.
Discussion
Scenario Six, referred to as “Dream Investment,” is considered favorable due to the fact that most of its drivers are in a favorable state. In contrast, the other scenarios are less favorable, with Scenario One identified as entirely unfavorable. In Scenario Six, healthcare financing through public-private partnerships occupies an optimal position. To realize this scenario, the government must create a secure and appealing environment that encourages investor participation. This requires the implementation of tailored fiscal and monetary policies specific to the healthcare sector. Exchange rate management and fiscal policy can play a pivotal role. If the exchange rate remains stable and financial policies are designed to facilitate investment and support industry growth, they can effectively attract investors. Moreover, regulatory transparency and predictability significantly contribute to building trust and encouraging investment. These conditions promote confidence among investors and private entities. Reducing bureaucratic obstacles and liberalizing private sector operations can further advance the growth and dynamism of the healthcare industry by creating additional opportunities for investment and expansion.
However, as Scenario Six also illustrates, excessive administrative bureaucracy and government-imposed price controls continue to pose challenges. To mitigate these issues, the government should adopt measures such as outsourcing selected functions, emphasizing competitive advantages, streamlining administrative chains of command, and delegating authority. Additionally, reducing price controls while subsidizing healthcare for the public and enabling open competition among hospitals can not only enhance service quality but also promote more competitive pricing.
Based on the findings of this study—including the macro-level categorization of drivers and the results of scenario analysis—it is recommended that future research focus on improving economic-financial factors under heightened environmental uncertainty, strengthening regulatory dimensions with an emphasis on information transparency, and developing strategies to streamline the public healthcare bureaucracy.
Research Limitations
- Geographical Limitation: This research was exclusively focused on experts in the healthcare sector of Kashan city and the supply chain of hospitals in this region; therefore, the generalizability of the findings to other regions of Iran with different economic, social, and cultural structures requires caution.
- Temporal Limitation: The research was conducted during the period from winter 2021 to spring 2023. Given the dynamism and rapid changes in Iran's economic, political, and social environment (especially exchange rate fluctuations, sanctions, and changes in government policies), some of the drivers and scenarios identified in this research may change over time and require updating.
- Data Limitation: Due to the confidentiality of information and the sensitive nature of some financial and economic data in the healthcare sector, access to all required data for the research was not possible, and the researchers were compelled to use expert opinions as a substitute for objective data.
Conclusion
This research, by identifying 21 drivers and extracting 13 key drivers, outlined 7 consistent scenarios for the future of financing through public-private partnership in Iran's healthcare supply chain. The "Dream Investment" scenario, as the most desirable scenario, indicates that exchange rate stability, transparency of laws and regulations, reduction of company monopolies, stability of government procedures, reduction of investment risk, and trust-building between the public and private sectors are the most critical factors for attracting investment. In contrast, mandatory pricing, administrative bureaucracy, and high taxes were identified as persistent structural barriers in all scenarios, highlighting the necessity of their reform. Given that 85% of the consistent scenarios lead to increased investment, policymakers are recommended to adopt coordinated monetary and fiscal policies, reduce administrative bureaucracy, replace mandatory pricing with competitive mechanisms, and provide treatment subsidies to the public to pave the way for the realization of the desirable scenario.
Declarations
Ethical considerations: This study was conducted following approval by the Research Ethics Committee of the University of Kashan (Ethics Approval Code: IR.KASHANU.REC.1402.018).
Funding: This research was conducted independently and without receiving any financial support.
Conflict of interest: The authors declare that there is no financial, organizational, or personal conflict of interest in connection with this study.
Authors’ contribution: Mohammadreza Safari: Data curation, Resources, Data management, Writing– original draft, Writing– review & editing, Visualization, Project administration, Fund acquisition
Esmaeil Mazroui Nasrabadi: Conceptualization, Study design, Methodology, Software, Validation, Data analysis, Writing– original draft, Writing– review & editing, Visualization, Supervision, Project administration, Fund acquisition, Final approval
All authors have read and approved the final version of the manuscript.
Consent for publication: Not applicable.
Data availability: Access to the data is available through the corresponding author upon reasonable request.
AI declaration: The authors used artificial intelligence (Deepseek-V3) for editing the English section of this article. All AI-edited content has been reviewed and approved by the authors.
Acknowledgements: Thank you to all the participants in this research.
Type of Study: Research |
Subject:
Health Services Management
Received: 2026/03/11 | Accepted: 2026/08/9
Received: 2026/03/11 | Accepted: 2026/08/9
References
1. Safari M, Mazroui Nasrabadi E. The future study of service-based financing in the healthcare supply chain. Journal of Health Administration 2024; 26 (3) :29-49. http://dx.doi.org/10.22034/26.3.29 [In Persian].
2. Erdebilli B, Sicakyuz C, Yilmaz İ. An integrated multiple-criteria decision-making and data envelopment analysis framework for efficiency assessment in sustainable healthcare systems. Healthcare Analytics 2024; 5, 100327. [DOI:10.1016/j.health.2024.100327]
3. Eldhose A. M. Pattern of health expenditure and utilization of health care services in Kerala- a perspective analysis. International Journal of Interdisciplinary and Multidisciplinary Research (IJIMR) 2024; 221-230. https://www.macollege.ac.in/Faculty-Profile/Dr-ELDHOSE-A-M/20
4. Khakimovna R. N. Principles of proper financing of investment processes. Web of Semantics: Journal of Interdisciplinary Science 2024; 2(5), 525-528. https://web.semanticjournals.org/
5. Antelli M. The influence of financing structure on professional sport clubs'performance in italian "lnp serie a2" LEAGUE (Doctoral dissertation, Vytautas Magnus University). 2024. https://hdl.handle.net/20.500.12259/260208
6. McGuire C. M, Kaiser J. L, Vian T, Nkabane-Nkholongo E, Nash T, Jack B. W, Scott N. A. Learning from the end of the public-private partnership for Lesotho's national referral hospital network. Annals of Global Health 2024; 90(1). [DOI:10.5334/aogh.4377]
7. Dove G, Kelly-Hanku A, Usurup J, O'Keeffe A, Scahill G, Craig A. Collaboration in a partnership for primary health care: a case study from Papua New Guinea. Global Health: Science and Practice 2024; 12(1): 1-11. [DOI:10.9745/GHSP-D-23-00040]
8. Isife C. T, Offorma G. C. Integrating public-private partnerships in primary health care delivery for sustainable inclusive development in Nigeria. Journal of the Nigerian academy Of education 2024; 19(1). https://journals.ezenwaohaetorc.org/
9. Bagenda B, Ndevu Z. Principal risks associated with public-private partnership projects in Uganda. Public Works Management & Policy 2024; 29(2), 183-230. [DOI:10.1177/1087724X231167326]
10. Chethan R. K, Balaji K. Exploring the effectiveness of public-private partnerships in propelling sustainable infrastructure development in India. In 2024 11th International Conference on Computing for Sustainable Global Development (INDIACom) 2024; 1675-1680. [DOI:10.23919/INDIACom61295.2024.10498387]
11. Jóhannesson O. A. Analysing risk and value in public-private partnerships: a quantitative analysis. master thesis, Reykjavik University. 2024. https://skemman.is/bitstream/1946/47710/3/Meistararitger%C3%B0___Oliver_Aron_Jo%CC%81hannesson-24.pdf
12. Yessenali A, Azretbergenova G, Izatullayeva B, Baibosynova G, Zhetibayev Z, Myrzaliev B, et al. Conceptual platform and applied aspects of interaction between government and business agencies in the Republic of Kazakhstan. Journal of Infrastructure, Policy and Development 2024; 8(5), 1-21. [DOI:10.24294/jipd.v8i5.3396]
13. Abdul S, Adeghe E. P, Adegoke B. O, Adegoke A. A, Udedeh E. H. Public-private partnerships in health sector innovation: Lessons from around the world. Magna Scientia Advanced Biology and Pharmacy 2024; 12(1), 045-059. [DOI:10.30574/msabp.2024.12.1.0032]
14. Hanif S, Nasir S, Hussain N, Zeb A. Public-private partnership in healthcare: an analysis of parents' perceived care quality in Pakistan's twin cities hospitals, Islamabad and Rawalpindi-a comparative cross-sectional study. Kurdish Studies 2024; 12(4), 969-974. [DOI:10.53555/ks.v12i4.3091]
15. Srivarathan A, Kristiansen M, Jensen A. N. Opportunities and challenges in public-private partnerships to reduce social inequality in health in upper-middle-income and high-income countries: a systematic review and meta-synthesis. BMJ open 2024; 14(1), e076209. [DOI:10.1136/bmjopen-2023-076209]
16. Nag A, Das N, Bose I. Quality of healthcare service in west bengal: the perspective of public private partnership model. Indian Journal of Industrial Relations 2024; 59(3): 426-441. https://www.publishingindia.com/public/archive/ijir/quality-of-healthcare-service-in-west-bengal-the-perspective-of-public-private-partnership-model
17. Morris G, Maliqi B, Lattof S. R, Strong J, Yaqub N. Private sector quality of care for maternal, new-born, and child health in low-and-middle-income countries: a secondary review. Frontiers in Global Women's Health 2024; 5, 1369792. [DOI:10.3389/fgwh.2024.1369792]
18. Samsudin M. F, Lim Y. C, Rochmah T. N, Dahlui M. Revisiting the policy implications of medical tourism in the post-covid-19 pandemic from a Malaysian perspective: a qualitative study. Cureus 2024;16(7). [DOI:10.7759/cureus.64308]
19. Boostaneh M, Mamaghani E. A, Zirak M, Abbasdost R, Fallah R. Burden of care and its relationship with sleep quality of cancer patients' caregivers: A descriptive-correlational study. International Journal of Africa Nursing Sciences 2024; 20, 100670. [DOI:10.1016/j.ijans.2024.100670]
20. Mokhtary S, Janati A, Yousefi M, Raei B, Moradi F. Challenges of hospital payment systems in Iran: results from a qualitative study. Ethiopian Journal of Health Sciences, 2024; 34(3). [DOI:10.4314/ejhs.v34i3.8]
21. Mousavi S, Alavi M, Delavari A, Poustchi H, Mohammadi Z, Malekzadeh R. Towards hepatitis C virus elimination in Iran: A blueprint for comprehensive strategies. Journal of Viral Hepatitis. 2024, 31(9): 565:572. [DOI:10.1111/jvh.13975]
22. Safari M, Mazroui Nasrabadi E. The future study of government funding in the healthcare supply chain: a scenario analysis approach. Manage Strat Health Syst 2023; 8 (3) :264-275.
https://doi.org/10.18502/mshsj.v8i3.14465 [DOI:10.18502/mshsj.v8i3.14465. [In Persian].]
23. Ganji Arjenaki, M. J, Mazroui Nasrabadi, E. Healthcare supply chain financing through public-private partnership: a strategic analysis of drivers. Journal of Asset Management and Financing, 2023; 11(4): 29-46. [DOI:10.22108/amf.2024.139148.1825 [In Persian].]
24. Raphael A, Isaac A, Agorsor MK. Healthcare financing and sustainability in Ghana: evidence from Ada Foah municipality. EPRA international journal of economics, business and management studies (EBMS) 2022; 9(4): 29-37. [DOI:10.36713/epra8831]
25. Al Mustanyir S. Government healthcare financing and dwindling oil prices: Any alternatives for OPEC countries?. Cogent Economics & Finance 2023; 11(1), 2166733. [DOI:10.1080/23322039.2023.2166733]
26. Braun, V., Clarke, V., Terry, G. Thematic analysis: a practical guide. SAGE Publications Ltd. 2021. [DOI:10.4135/9781036232078.n9]
27. Guba, E. G., Lincoln, Y. S. Epistemological and methodological bases of naturalistic inquiry. ECTJ 1982; 30(4), 233-252. [DOI:10.1007/BF02765185]
28. Ayre C, Scally AJ. Critical values for Lawshe's content validity ratio: revisiting the original methods of calculation. Measurement and evaluation in counseling and development. 2014 Jan;47(1):79-86. [DOI:10.1177/0748175613513808]
29. Safari M, Nasrabadi EM. The future study of government funding in the healthcare supply chain: a scenario analysis approach. Quarterly Journal of Management Strategies in Health System. 2023;8(3):264-275. http://dx.doi.org/10.18502/mshsj.v8i3.14465 [DOI:10.18502/mshsj.v8i3.14465]
30. Otchere G, Fusheini A, Gauld R, Ankomah SE, Sullivan T, Penno E. Facilitators and barriers of public-private partnerships for universal health coverage in sub-Saharan Africa: a scoping review. Health Policy Plan. 2026;41(1):81-93. [DOI:10.1093/heapol/czaf100]
31. Le SM, Govindaraj R, Bredenkamp C. Public-private partnerships for health in vietnam: issues and options. Washington (DC): World Bank Group. [DOI:10.1596/978-1-4648-1574-4]
32. Suchman L, Hart E, Montagu D. Public-private partnerships in practice: collaborating to improve health finance policy in Ghana and Kenya. Health Policy Plan. 2018;33(7):777-785. [DOI:10.1093/heapol/czy053]
33. Iyer V, Sidney K, Mehta R, Mavalankar D, De Costa A. Characteristics of private partners in Chiranjeevi Yojana, a public-private partnership to promote institutional births in Gujarat, India: lessons for universal health coverage. PLoS One. 2017;12(10):e0185739. [DOI:10.1371/journal.pone.0185739]
34. Mohanan M, Bauhoff S, La Forgia G, Babiarz KS, Singh K, Miller G. Effect of Chiranjeevi Yojana on institutional deliveries and neonatal and maternal outcomes in Gujarat, India: a difference-in-differences analysis. Bull World Health Organ. 2014;92(3):187-194. doi:10.2471/BLT.13.124644.
https://doi.org/10.2471/BLT.13.124644 [DOI:10.2471/blt.13.124644]
35. Williamson OE. The economic institutions of capitalism. New York: Free Press; 1985.
Send email to the article author
| Rights and permissions | |
 |
This work is licensed under a Creative Commons Attribution-NonCommercial 4.0 International License. |
Site Keywords
Health, Administration, Scientific Article, Iran University of Medical Sciences,
